 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
Post-SSRI Sexual Symptoms After Discontinuation: Definitions, Evidence, and Uncertainty
Key answer
A careful explanation of persistent sexual symptoms reported after SSRI or SNRI discontinuation, recognized warnings, major evidence gaps, and clinical evaluation. The central safety principle is: Post-SSRI sexual dysfunction (PSSD), also used for persistent sexual dysfunction after some serotonergic antidepressants. [1–3]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| Working term | Post-SSRI sexual dysfunction (PSSD), also used for persistent sexual dysfunction after some serotonergic antidepressants. |
| Reported domains | Genital sensation, libido, arousal, erection or lubrication, orgasm, and pleasure. |
| What regulators recognize | Reports can persist after treatment stops; product warnings have been updated in some regions. |
| What remains unknown | Incidence, mechanism, predictors, diagnostic biomarkers, natural history, and proven treatment. |
Evidence basis and uncertainty
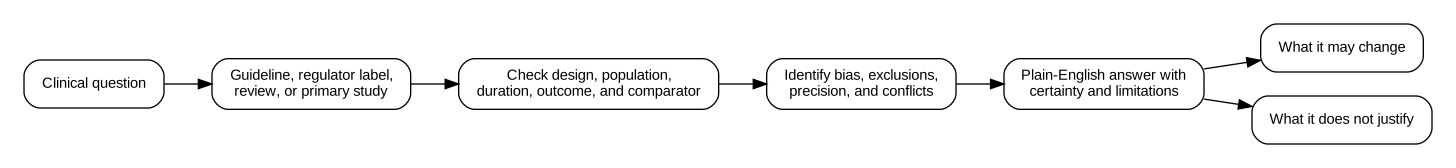
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–3]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Regulatory safety communication | Recognizes reports of persistent sexual dysfunction; incidence, risk factors, and mechanism remain uncertain. |
| 2 | Systematic review | Shows that the persistent-withdrawal evidence base remains sparse and methodologically limited. |
| 3 | Guideline | Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
Use the term as a description, not a certainty
PSSD is used for sexual symptoms that begin during or after serotonergic antidepressant exposure and persist after discontinuation. Definitions vary across publications. A careful article should not imply that every post-treatment sexual problem has the same mechanism or that diagnosis can be made from an online checklist.
What symptoms are reported
Reports include reduced genital sensation, reduced libido, erectile or lubrication difficulty, delayed or absent orgasm, reduced pleasure, and emotional blunting. Symptoms can be distressing and may affect relationships, identity, and mental health.
Why alternative explanations must be evaluated
Depression, anxiety, trauma, endocrine disorders, menopause, vascular disease, neurologic illness, pelvic conditions, cancer treatment, other medicines, substance use, and relationship context can affect sexual function. More than one factor may be present.
What the evidence can support
Regulators have recognized persistent reports sufficiently to update warnings in some jurisdictions. Case reports, pharmacovigilance data, surveys, and small studies support a signal. These designs cannot estimate incidence reliably or establish one mechanism.
What treatment claims should be avoided
No supplement, hormone, device, medication, or reinstatement strategy has high-certainty evidence as a universal cure. Interventions may have adverse effects or worsen other symptoms. Clinical evaluation should be individualized, and unsupported commercial claims should be treated cautiously.
How to document the problem
Record function before antidepressant treatment, changes during treatment, timing relative to dose reduction, specific domains affected, other medicines, endocrine and medical history, and the effect on distress and relationships. This improves differential diagnosis and future research quality.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- Immediate self-harm risk related to distress-
New neurologic deficits, saddle anesthesia, bladder dysfunction, or severe pelvic pain
-
Symptoms are being treated with unmonitored hormones or interacting medicines
-
A commercial treatment claims a guaranteed cure without controlled evidence
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- What is the current indication and treatment goal?
- Which alternative explanations for the symptoms need assessment?
- What is the exact medication, formulation, timing, and most recent change?
- Which outcome should be monitored before another change is considered?
- What are the urgent warning signs and the fastest route back to the clinical team?
Frequently asked questions
Is PSSD officially recognized?
Several regulators have added warnings about persistent sexual dysfunction after SSRI or SNRI discontinuation. Recognition of reports does not settle incidence or mechanism.
Is genital numbness diagnostic?
It is a reported feature but not a stand-alone diagnostic test. Neurologic, endocrine, pelvic, medication, and psychological causes should be assessed.
Is there a proven cure?
No universal evidence-based cure has been established. Be cautious with high-cost or high-risk treatments marketed as guaranteed.
Can symptoms improve over time?
Improvement is reported, as is persistence, but reliable prognosis estimates are lacking.
Regional and formulation note
Guidelines, labels, formulations, and care pathways vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
European and Australian regulator communications on persistent sexual dysfunction after SSRI/SNRI discontinuation. Evidence type: Regulatory safety communication. Use in this article: Recognizes reports of persistent sexual dysfunction; incidence, risk factors, and mechanism remain uncertain.
-
Rennwald K, Hengartner MP. Persistent post-withdrawal symptoms after antidepressants: systematic review. 2025. Evidence type: Systematic review. Use in this article: Shows that the persistent-withdrawal evidence base remains sparse and methodologically limited.
-
NICE. Medicines associated with dependence or withdrawal symptoms: safe prescribing and withdrawal management for adults (NG215). Evidence type: Guideline. Use in this article: Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.