 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
CBT-I During a Sleeping-Pill or Benzodiazepine Taper: What the Evidence Supports
Key answer
How cognitive behavioral therapy for insomnia can support sleep-medication or benzodiazepine reduction without promising that it prevents every withdrawal symptom. The central safety principle is: A multicomponent treatment usually including stimulus control, sleep scheduling or restriction, cognitive strategies, and relapse prevention. [1–4]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| CBT-I | A multicomponent treatment usually including stimulus control, sleep scheduling or restriction, cognitive strategies, and relapse prevention. |
| What it can target | Chronic insomnia mechanisms, sleep-related fear, time in bed, irregular scheduling, and unhelpful compensatory behaviors. |
| What it cannot guarantee | Prevention of all medication withdrawal, seizures, delirium, mood relapse, or another sleep disorder. |
| Important distinction | Sleep hygiene alone is not equivalent to CBT-I. |
Evidence basis and uncertainty
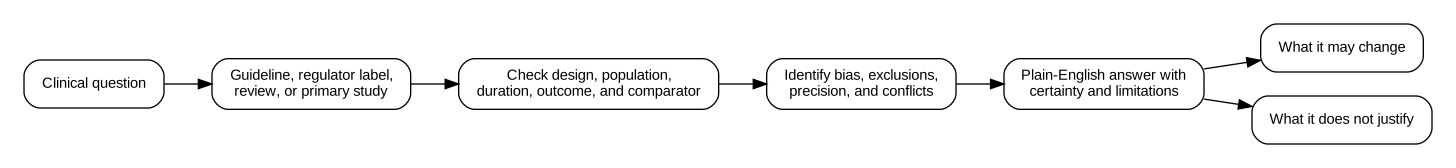
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–4]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Clinical practice guideline | Strongly recommends multicomponent CBT-I for chronic insomnia; sleep hygiene alone is not equivalent to CBT-I. |
| 2 | Clinical practice guideline | Conditional recommendations based on low-certainty evidence; treatment preferences and clinical context remain important. |
| 3 | Multisociety clinical practice guideline | Recommends individualized, generally gradual reductions, monitoring, and avoidance of abrupt discontinuation in physically dependent patients. |
| 4 | Guideline | Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
Why insomnia treatment and medication reduction are separate tasks
A hypnotic may be reduced while chronic insomnia remains untreated. Conversely, insomnia during withdrawal may improve as the medication plan stabilizes but still benefit from behavioral treatment. Separating the tasks avoids using each bad night as proof that the taper failed or that the medication must be escalated.
What CBT-I includes
Multicomponent CBT-I typically includes a structured sleep assessment, stimulus control, a carefully prescribed sleep window, cognitive work on sleep beliefs, and relapse prevention. Relaxation may be included. Generic advice about screens, caffeine, and bedroom temperature is sleep hygiene, not a complete CBT-I program.
Evidence during hypnotic deprescribing
Trials and guidelines support behavioral treatment as part of insomnia care and benzodiazepine-receptor-agonist deprescribing. Results vary by population, medication, therapist access, and whether the outcome is medication cessation, sleep, or long-term relapse. CBT-I can improve the chance of successful reduction for some people, but it does not eliminate medication-specific risk.
Adapting CBT-I during instability
Standard sleep restriction can temporarily increase sleepiness and requires clinical adaptation for bipolar disorder, seizure disorders, untreated sleep apnea, fall risk, safety-sensitive work, pregnancy, frailty, or acute medical illness. A trained clinician can use a gentler sleep-compression approach or defer components when needed.
What to track
Track sleep opportunity, estimated sleep onset, awakenings, final wake time, naps, daytime sleepiness, function, medication timing, alcohol or cannabis, and withdrawal symptoms. Consumer wearables can add trends but should not overrule the sleep diary or clinical assessment.
2026 evidence and topic-cluster update
Current evidence supports CBT-I as an adjunct to a supervised taper, not as permission to accelerate one. The 2024 masked-taper trial and recent deprescribing studies show that behavioral support and taper design can affect discontinuation outcomes, while ASAM still prioritizes a symptom-responsive medication plan. This page targets tapering; for the full treatment itself, see CBT-I: Components, Effectiveness, Safety, and What It Is Not.
Related focused guides cover digital vs therapist-led CBT-I, CBT-I with sleep apnea and PAP, and bipolar-specific adaptation.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- Severe daytime sleepiness with driving or workplace risk-
Mania, psychosis, seizure, delirium, or immediate self-harm risk
-
Possible untreated sleep apnea with significant breathing symptoms
-
A rigid sleep-restriction plan is being used despite a contraindication or acute medical instability
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- What is the current indication and treatment goal?
- Which alternative explanations for the symptoms need assessment?
- What is the exact medication, formulation, timing, and most recent change?
- Which outcome should be monitored before another change is considered?
- What are the urgent warning signs and the fastest route back to the clinical team?
Frequently asked questions
Will CBT-I stop rebound insomnia?
It may improve coping and chronic insomnia mechanisms, but it cannot guarantee that short-term rebound will not occur.
Can I do CBT-I from an app?
Validated digital CBT-I can improve access, but quality varies and complex medical or psychiatric conditions may require clinician involvement.
Is sleep restriction safe during a benzodiazepine taper?
It may need adaptation when there is severe sleep deprivation, bipolar or seizure risk, falls, driving, or other safety concerns. Use a trained clinician.
Should CBT-I start before the taper?
Often that is practical, but timing should reflect access, urgency, and individual readiness. The evidence does not establish one mandatory sequence.
Regional and formulation note
Guidelines, labels, formulations, and care pathways vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
American Academy of Sleep Medicine. Behavioral and psychological treatments for chronic insomnia disorder in adults. 2021. Evidence type: Clinical practice guideline. Use in this article: Strongly recommends multicomponent CBT-I for chronic insomnia; sleep hygiene alone is not equivalent to CBT-I.
-
American Academy of Sleep Medicine. Combination treatment for chronic insomnia disorder in adults. 2026. Evidence type: Clinical practice guideline. Use in this article: Conditional recommendations based on low-certainty evidence; treatment preferences and clinical context remain important.
-
ASAM and partner societies. Joint Clinical Practice Guideline on Benzodiazepine Tapering. 2025. Evidence type: Multisociety clinical practice guideline. Use in this article: Recommends individualized, generally gradual reductions, monitoring, and avoidance of abrupt discontinuation in physically dependent patients.
-
NICE. Medicines associated with dependence or withdrawal symptoms: safe prescribing and withdrawal management for adults (NG215). Evidence type: Guideline. Use in this article: Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.