 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
CBT-I for Bipolar Disorder: Why Adaptation and Mood Monitoring Matter
Key answer
Cognitive behavioral therapy for insomnia (CBT-I) is the recommended first-line treatment for chronic insomnia. It combines assessment, stimulus control, sleep scheduling or sleep-restriction methods, cognitive strategies, and relapse prevention. The treatment can be delivered in person, by telehealth, in groups, or through validated digital programs, but the components and level of supervision may need adaptation when another condition changes the safety of sleep loss or the interpretation of symptoms. [1–3]
At a glance
| Question | Evidence-based answer |
|---|---|
| Is CBT-I the same as sleep hygiene? | No. Sleep hygiene is supportive education; multicomponent CBT-I is an active treatment. [1] |
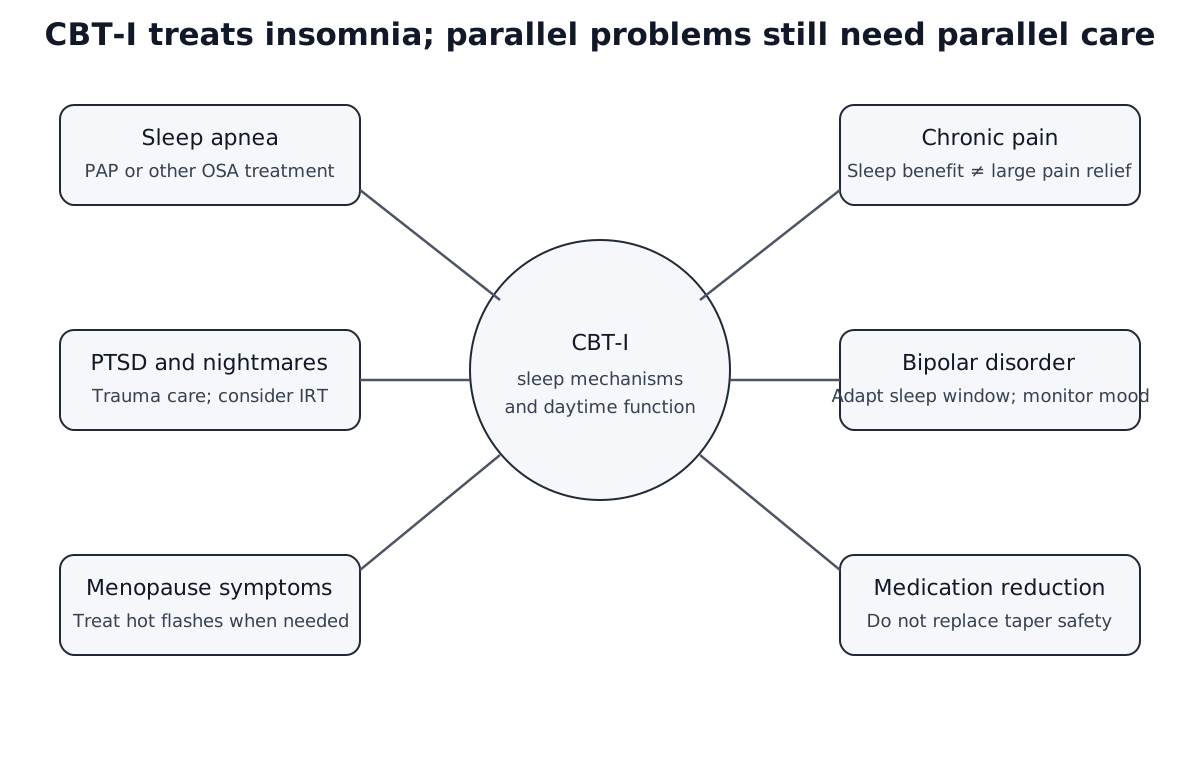
| Does it work with comorbid illness? | Often yes, and guidelines recommend it across many comorbidities, but parallel illnesses still need parallel care. [2,3] |
| Can it be digital? | Validated digital CBT-I can be effective; therapist support, engagement, and complexity influence results. |
| Is sleep restriction always used unchanged? | No. Time-in-bed reduction may need adaptation for bipolar disorder, seizure risk, excessive sleepiness, falls, pregnancy, or unstable illness. [3] |
| Does CBT-I guarantee medication discontinuation or cure another condition? | No. It treats insomnia mechanisms and may support other goals, but it does not erase medication-specific risk or replace other treatment. |
What CBT-I includes
A full program usually begins with a sleep and medical history plus a sleep diary. Stimulus control strengthens the connection between bed and sleep. Sleep scheduling or sleep restriction therapy reduces excessive time awake in bed and later expands the sleep window as sleep consolidates. Cognitive strategies test catastrophic predictions and unhelpful monitoring. Relapse-prevention planning prepares for travel, illness, stress, medication changes, or symptom flares. Relaxation and sleep-hygiene education may support the program but do not replace the core treatment. [1–3]
Why standard CBT-I may need modification
Sleep loss can precede or trigger mania or hypomania in vulnerable people. Standard sleep-restriction therapy deliberately limits time in bed for a period, so bipolar-specific protocols often protect a minimum sleep opportunity, emphasize regular circadian timing, monitor mood and energy closely, and coordinate with the psychiatrist.
A small pilot randomized trial of a bipolar-specific CBT-I modification found better sleep and a favorable signal for fewer days in bipolar episodes over follow-up, but it was designed to estimate feasibility and effect sizes rather than prove a definitive relapse-prevention effect. A mixed mood-disorder trial did not find a primary insomnia group-by-time advantage but reported some secondary benefits. [4,5]
Warning signs that change the plan
Reduced need for sleep is different from being tired but unable to sleep. New elevated or irritable mood, racing thoughts, pressured speech, unusual confidence, increased goal-directed activity, impulsive spending or risk-taking, psychosis, or rapidly falling sleep need requires prompt psychiatric assessment. It should not be managed by tightening the sleep window.
Bipolar-adapted principles
| Standard element | Possible adaptation |
|---|---|
| Sleep restriction | Use sleep compression or a protected minimum sleep opportunity. |
| Fixed wake time | Retain regularity while avoiding excessive deprivation. |
| Stimulus control | Preserve, but review nighttime safety and agitation. |
| Cognitive work | Add beliefs about mania, medication, and sleep-related fear. |
| Monitoring | Add daily mood, energy, impulsivity, and need-for-sleep tracking. |
Safety and adaptation
Transient sleepiness can occur when time in bed is compressed. A trained clinician should review driving, safety-sensitive work, falls, untreated sleep apnea, uncontrolled seizure disorder, bipolar disorder, active substance-use problems, acute suicidality or psychosis, pregnancy or postpartum demands, and unstable medical illness. The response may be a gentler sleep-compression approach, a wider initial sleep window, closer monitoring, treatment of another disorder first, or referral to a behavioral sleep medicine specialist. [3]
What to track
Track bedtime, final wake time, estimated sleep onset, awakenings, naps, daytime sleepiness, functional safety, relevant symptoms, medication timing, alcohol or other sedatives, and adherence to the agreed components. Wearables can show trends but do not diagnose insomnia or sleep apnea and should not overrule a clinical assessment.
Questions to take to the clinical team
- Has insomnia disorder been assessed, or could another sleep disorder explain the pattern?
- Which CBT-I components are appropriate now, and which need adaptation?
- What outcome will be monitored: insomnia severity, function, medication use, mood, pain, PAP use, or another goal?
- What symptoms require stopping the self-guided plan and contacting the team?
- Is the digital or group program validated, and is clinician support available if progress stalls?
Frequently asked questions
Is CBT-I contraindicated in bipolar disorder?
No, but standard components often need bipolar-specific adaptation and coordination with psychiatric care.
What is the difference between insomnia and reduced need for sleep?
With insomnia, a person usually wants sleep and feels impaired. In hypomania or mania, the person may sleep less without feeling tired and may have increased energy or behavioral change.
Can CBT-I replace a mood stabilizer?
No. It treats insomnia and circadian behaviors; medication decisions remain with the psychiatric prescriber.
What should be tracked?
Sleep timing, sleep opportunity, mood, energy, impulsivity, medication adherence, and any signs of emerging mania.
References
-
Edinger JD, et al. Behavioral and psychological treatments for chronic insomnia disorder in adults: an American Academy of Sleep Medicine clinical practice guideline. 2021. Evidence type: Clinical practice guideline. Use: Strong recommendation for multicomponent CBT-I; sleep hygiene alone is not an adequate stand-alone treatment.
-
Riemann D, et al. The European Insomnia Guideline: an update on diagnosis and treatment of insomnia 2023. Evidence type: European guideline. Use: CBT-I as first-line treatment in adults of any age, including comorbidities, in-person or digitally.
-
VA/DoD. Clinical Practice Guideline for the Management of Chronic Insomnia Disorder and Obstructive Sleep Apnea. 2025. Evidence type: National clinical practice guideline. Use: Delivery options, diagnostic screening, and situations requiring adaptation or delay.
-
Harvey AG, et al. Treating insomnia improves mood state, sleep, and functioning in bipolar disorder: pilot randomized trial. 2015. Evidence type: Small pilot randomized trial. Use: Feasibility, sleep benefit, and preliminary mood-course signal.
-
Nurse-administered CBT-I as early intervention in first-episode mood disorders: randomized trial. 2023. Evidence type: Randomized trial. Use: Mixed primary and secondary outcomes; not treated as definitive bipolar evidence.
-
Transdiagnostic sleep and circadian intervention in depression, ADHD, or bipolar disorder: randomized trial. 2025. Evidence type: Mixed-diagnosis randomized trial. Use: Emerging evidence; bipolar-specific conclusions remain limited.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.