 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
Why 2024 and 2025 Antidepressant Withdrawal Meta-Analyses Look Reassuring—Yet Do Not End the Debate
Key answer
The 2024 and 2025 meta-analyses provide useful lower average estimates and placebo-controlled symptom comparisons, but their study mix, treatment duration, follow-up, and participant selection limit conclusions about long-term and persistent withdrawal. The practical interpretation must remain within the population, duration, formulation, and outcomes that were actually studied. [1–4]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| One-sentence finding | The 2024 and 2025 meta-analyses provide useful lower average estimates and placebo-controlled symptom comparisons, but their study mix, treatment duration, follow-up, and participant selection limit conclusions about long-term and persistent withdrawal. [1–4] |
| Evidence base | The 2024 review combined 79 studies and estimated medication-attributable discontinuation symptoms after accounting for nonspecific symptoms. The 2025 review focused on symptom scales and placebo or continuation comparisons, finding a small average increase at one week. Both syntheses included heterogeneous drugs and often relatively short treatment exposure. [1–4] |
| Main uncertainty | Short follow-up can miss delayed symptoms, especially for long-half-life medicines. Selected trials underrepresent long-term use, severe prior withdrawal, complex comorbidity, and self-directed tapers. Mean symptom counts can hide a small group with major functional impairment. Several widely used drugs have limited data. [1–4] |
| Practice implication | Counsel patients with ranges and uncertainty rather than a single headline percentage. Ask about duration, drug, dose, prior missed-dose reactions, and goals. Use current guidance for individualized gradual reduction and monitor function, not only checklist totals. [1–4] |
| Not justified | The reviews do not justify dismissing severe or persistent cases, promising a brief course, or using short trial averages to prescribe a fixed taper. They also do not justify presenting selected survey estimates as population incidence. [1–4] |
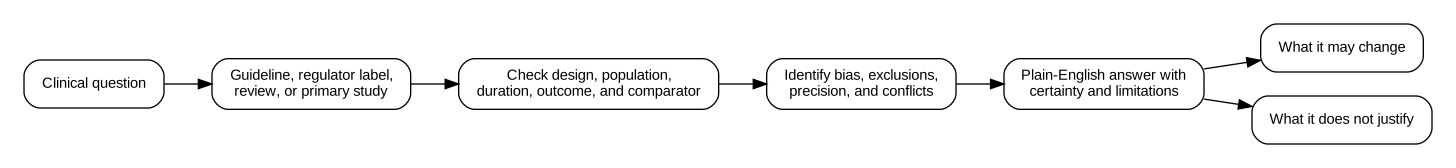
Evidence basis and uncertainty
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–4]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Systematic review and meta-analysis | Estimated incidence after accounting for nonspecific symptoms; important limits include treatment duration and study design. |
| 2 | Systematic review and meta-analysis | Placebo-controlled symptom estimates, largely from relatively short trials; does not settle long-term or persistent-withdrawal questions. |
| 3 | Observational study | Patient-reported associations; useful for hypothesis generation but vulnerable to selection and recall bias. |
| 4 | Systematic review | Shows that the persistent-withdrawal evidence base remains sparse and methodologically limited. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
The finding in one sentence
The 2024 and 2025 meta-analyses provide useful lower average estimates and placebo-controlled symptom comparisons, but their study mix, treatment duration, follow-up, and participant selection limit conclusions about long-term and persistent withdrawal.
Why this question matters
Headlines can polarize the discussion into “withdrawal is common and severe” versus “withdrawal is mostly mild.” A method-focused comparison allows both the average trial signal and severe patient experiences to be represented accurately.
What evidence was reviewed
The 2024 review combined 79 studies and estimated medication-attributable discontinuation symptoms after accounting for nonspecific symptoms. The 2025 review focused on symptom scales and placebo or continuation comparisons, finding a small average increase at one week. Both syntheses included heterogeneous drugs and often relatively short treatment exposure.
What the studies found
The reviews suggest that many people do not experience severe symptoms and that nonspecific symptoms account for part of reported incidence. They also identify drug differences and substantial uncertainty. Their mean results do not describe the tail of the distribution or provide a prognosis for a long-term user with previous withdrawal.
Key limitations and sources of uncertainty
Short follow-up can miss delayed symptoms, especially for long-half-life medicines. Selected trials underrepresent long-term use, severe prior withdrawal, complex comorbidity, and self-directed tapers. Mean symptom counts can hide a small group with major functional impairment. Several widely used drugs have limited data.
What this may change in practice
Counsel patients with ranges and uncertainty rather than a single headline percentage. Ask about duration, drug, dose, prior missed-dose reactions, and goals. Use current guidance for individualized gradual reduction and monitor function, not only checklist totals.
What the evidence does not justify
The reviews do not justify dismissing severe or persistent cases, promising a brief course, or using short trial averages to prescribe a fixed taper. They also do not justify presenting selected survey estimates as population incidence.
What research should do next
Prospective representative cohorts should enroll before tapering, stratify by duration and drug, use standardized symptom and function outcomes, and follow participants for at least months with independent relapse adjudication.
Funding and conflict-of-interest note
Drug-development studies are often sponsored by manufacturers, while guideline panels and independent reviews can also include authors with industry relationships. Publication should list the funding source and declared conflicts for every pivotal study. A declared conflict does not invalidate a result, but it raises the importance of protocol registration, complete outcome reporting, independent replication, and separation of evidence from promotional language.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- A trial result is described as proof for populations, durations, doses, or combinations that were not studied-
Absence of a detected signal is rewritten as a categorical absence-of-risk claim
-
A network meta-analysis is presented as a head-to-head randomized comparison
-
Regulatory approval in one country is described as global approval
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- Does this evidence apply to my diagnosis, age, treatment duration, formulation, and other medications?
- Was the finding based on a randomized comparison, an indirect comparison, an observational study, or mechanistic modeling?
- Were withdrawal, relapse, function, serious adverse events, and long-term outcomes measured directly?
- What was not studied, and what uncertainty remains for my situation?
- Would this finding actually change a clinical decision, or only support further research?
Frequently asked questions
Which meta-analysis is correct?
Both can be useful because they use different methods. Their results should be interpreted for the populations and outcomes included.
Why does one symptom on a scale matter?
An average of one symptom can be small at population level while still hiding important individual variation.
Did the studies include long-term users?
Some did, but long-term and highly withdrawal-sensitive users were not represented well enough to settle that subgroup.
Should severe anecdotes be ignored?
No. They identify harms and research gaps, but cannot estimate prevalence on their own.
Regional and formulation note
Approval status, labels, and clinical practice vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
Henssler J, et al. Incidence of antidepressant discontinuation symptoms: a systematic review and meta-analysis. The Lancet Psychiatry. 2024. Evidence type: Systematic review and meta-analysis. Use in this article: Estimated incidence after accounting for nonspecific symptoms; important limits include treatment duration and study design.
-
Kalfas M, et al. Incidence and Nature of Antidepressant Discontinuation Symptoms: A Systematic Review and Meta-Analysis. JAMA Psychiatry. 2025. Evidence type: Systematic review and meta-analysis. Use in this article: Placebo-controlled symptom estimates, largely from relatively short trials; does not settle long-term or persistent-withdrawal questions.
-
Horowitz MA, et al. Antidepressant withdrawal and duration of use: observational evidence. 2025. Evidence type: Observational study. Use in this article: Patient-reported associations; useful for hypothesis generation but vulnerable to selection and recall bias.
-
Rennwald K, Hengartner MP. Persistent post-withdrawal symptoms after antidepressants: systematic review. 2025. Evidence type: Systematic review. Use in this article: Shows that the persistent-withdrawal evidence base remains sparse and methodologically limited.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.