 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
Protracted Antidepressant Withdrawal: What the Evidence Shows—and What It Cannot Yet Tell Us
Key answer
A balanced review of persistent symptoms after antidepressant reduction, the limits of current evidence, competing explanations, and appropriate clinical evaluation. The central safety principle is: Symptoms that begin or intensify after antidepressant reduction and persist beyond the usual short observation windows. [1–5]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| What is being described | Symptoms that begin or intensify after antidepressant reduction and persist beyond the usual short observation windows. |
| What is established | Persistent patient-reported cases exist and deserve clinical attention. |
| What is uncertain | Incidence, diagnostic criteria, mechanisms, predictors, natural history, and best treatment. |
| Major research problem | Selection bias, recall bias, lack of controls, short trials, variable definitions, and overlap with relapse or medical illness. |
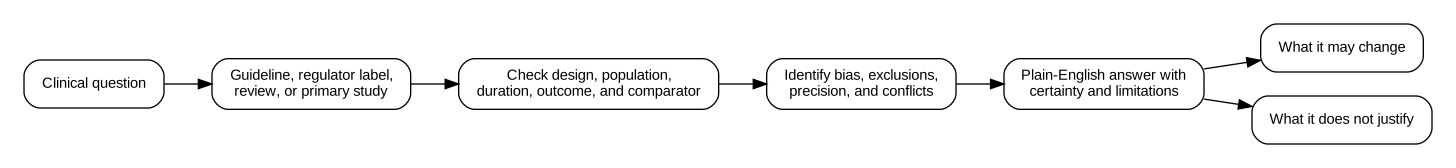
Evidence basis and uncertainty
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–5]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Systematic review | Shows that the persistent-withdrawal evidence base remains sparse and methodologically limited. |
| 2 | Systematic review and meta-analysis | Estimated incidence after accounting for nonspecific symptoms; important limits include treatment duration and study design. |
| 3 | Systematic review and meta-analysis | Placebo-controlled symptom estimates, largely from relatively short trials; does not settle long-term or persistent-withdrawal questions. |
| 4 | Observational study | Patient-reported associations; useful for hypothesis generation but vulnerable to selection and recall bias. |
| 5 | Guideline | Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
Why terminology is difficult
“Protracted withdrawal,” “persistent withdrawal,” and “post-acute withdrawal syndrome” are used inconsistently. RxDown uses persistent or protracted antidepressant withdrawal symptoms as a descriptive term, not a fully validated diagnosis. The phrase should identify a research and clinical problem without claiming a proven mechanism.
What systematic reviews find
Recent reviews identify reports of symptoms lasting months or longer, but the evidence base is small and often consists of selected surveys, case series, or studies without comparison groups. Conventional discontinuation trials usually follow participants for days or weeks and may exclude long-term or highly sensitive users, so they are poorly designed to estimate persistent outcomes.
Why incidence estimates cannot be combined casually
A placebo-controlled trial of short treatment, a general-population survey, and a self-selected withdrawal community answer different questions. They differ in treatment duration, drug mix, taper method, symptom definition, recruitment, and follow-up. A high rate in a selected survey and a lower average rate in a short trial can both be internally valid for their populations.
Clinical evaluation still matters
Persistent dizziness, sensory symptoms, insomnia, cognitive complaints, autonomic symptoms, pain, or mood changes can have multiple causes. Evaluation should consider relapse, sleep disorders, endocrine or neurologic disease, anemia, infection, substance effects, menopause, long COVID, other medications, and functional impairment. Recognizing uncertainty is not the same as dismissing the symptoms.
What treatment evidence is missing
There are no high-certainty trials that establish a universal reinstatement window, supplement regimen, diet, exercise protocol, or medication treatment for persistent withdrawal. Supportive care should be individualized and should avoid interventions that add avoidable adverse effects or new dependence.
Research priorities
Better studies need prospective enrollment before tapering, long-term users, standardized withdrawal and function measures, active monitoring beyond several months, drug- and formulation-specific data, clear relapse adjudication, and transparent inclusion of severe outcomes. Patient involvement in outcome design is essential.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- Immediate self-harm risk, psychosis, or mania-
New focal neurologic deficit, seizure, fainting, or severe confusion
-
Severe weight loss, dehydration, or inability to perform basic self-care
-
Symptoms attributed to withdrawal without evaluation of a plausible urgent medical cause
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- What is the current indication and treatment goal?
- Which alternative explanations for the symptoms need assessment?
- What is the exact medication, formulation, timing, and most recent change?
- Which outcome should be monitored before another change is considered?
- What are the urgent warning signs and the fastest route back to the clinical team?
Frequently asked questions
Does current evidence prove that protracted withdrawal is rare?
No. Existing studies are not well designed to estimate incidence in long-term users. They also do not prove that most persistent symptoms are withdrawal.
Does a normal test mean the symptoms are not real?
No. Normal tests can rule out some dangerous or treatable conditions but do not invalidate symptoms. They also do not establish a withdrawal mechanism.
Is reinstatement proven to work?
No universal rule is established. Potential benefit and risk depend on the medicine, time since reduction, current symptoms, prior response, and other clinical factors.
Should the term PAWS be used?
It is widely recognized in some communities but is not consistently defined for antidepressants. Use a descriptive definition and state the evidence limits.
Regional and formulation note
Guidelines, labels, formulations, and care pathways vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
Rennwald K, Hengartner MP. Persistent post-withdrawal symptoms after antidepressants: systematic review. 2025. Evidence type: Systematic review. Use in this article: Shows that the persistent-withdrawal evidence base remains sparse and methodologically limited.
-
Henssler J, et al. Incidence of antidepressant discontinuation symptoms: a systematic review and meta-analysis. The Lancet Psychiatry. 2024. Evidence type: Systematic review and meta-analysis. Use in this article: Estimated incidence after accounting for nonspecific symptoms; important limits include treatment duration and study design.
-
Kalfas M, et al. Incidence and Nature of Antidepressant Discontinuation Symptoms: A Systematic Review and Meta-Analysis. JAMA Psychiatry. 2025. Evidence type: Systematic review and meta-analysis. Use in this article: Placebo-controlled symptom estimates, largely from relatively short trials; does not settle long-term or persistent-withdrawal questions.
-
Horowitz MA, et al. Antidepressant withdrawal and duration of use: observational evidence. 2025. Evidence type: Observational study. Use in this article: Patient-reported associations; useful for hypothesis generation but vulnerable to selection and recall bias.
-
NICE. Medicines associated with dependence or withdrawal symptoms: safe prescribing and withdrawal management for adults (NG215). Evidence type: Guideline. Use in this article: Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.