 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
Why Antidepressant Withdrawal Studies Disagree
Key answer
Why antidepressant withdrawal estimates differ across randomized trials, meta-analyses, surveys, and long-term user studies—and how to read the numbers responsibly. The central safety principle is: Strong control of nonspecific symptoms, but often short treatment and short follow-up. [1–5]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| Randomized discontinuation trial | Strong control of nonspecific symptoms, but often short treatment and short follow-up. |
| General-population survey | Broader real-world use, but recall and attribution are difficult. |
| Self-selected withdrawal survey | Captures severe and persistent experiences, but cannot estimate population incidence. |
| Meta-analysis | Combines studies, but the result inherits differences and limitations of included designs. |
| Best interpretation | Ask which population, medication, duration, taper, outcome, and follow-up the number actually describes. |
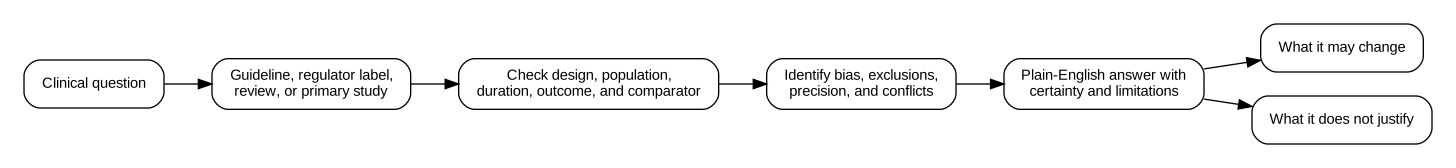
Evidence basis and uncertainty
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–5]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Systematic review and meta-analysis | Estimated incidence after accounting for nonspecific symptoms; important limits include treatment duration and study design. |
| 2 | Systematic review and meta-analysis | Placebo-controlled symptom estimates, largely from relatively short trials; does not settle long-term or persistent-withdrawal questions. |
| 3 | Observational study | Patient-reported associations; useful for hypothesis generation but vulnerable to selection and recall bias. |
| 4 | Systematic review | Shows that the persistent-withdrawal evidence base remains sparse and methodologically limited. |
| 5 | Systematic review and network meta-analysis | Supports slow tapering combined with psychological support for relapse prevention, while certainty varies and withdrawal-specific outcomes remain incomplete. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
Different studies ask different questions
“How many people report any symptom after stopping?” is not the same as “How many symptoms are caused by stopping after subtracting placebo symptoms?” Neither is the same as “How many long-term users have severe or persistent difficulty?” A single percentage cannot answer all three.
Treatment duration and participant selection
Many randomized trials involve weeks or months of treatment and exclude people with medical complexity, prior severe withdrawal, substance use, or high suicide risk. Surveys may include years of exposure and people motivated to report a difficult experience. The populations are not exchangeable.
How symptoms are defined
Some studies count any new symptom; others use the Discontinuation-Emergent Signs and Symptoms scale, a severity threshold, clinician judgment, or functional impairment. Different checklists include different sensory, gastrointestinal, sleep, mood, and neurologic symptoms.
Placebo and nocebo effects
Symptoms also occur in people who continue treatment or stop placebo. Placebo-controlled comparisons help estimate medication-attributable effects. They do not erase genuine individual withdrawal, and they may underrepresent delayed or long-duration outcomes if follow-up is short.
Relapse and withdrawal can be misclassified
Mood or anxiety recurrence can be counted as withdrawal; withdrawal-related anxiety or low mood can be counted as relapse. The two can coexist. Better studies need adjudication based on timing, symptom quality, prior illness pattern, and longer follow-up.
How RxDown should report the evidence
Report the design, population, treatment duration, taper method, follow-up, absolute numbers, and uncertainty. Do not place a survey estimate and a placebo-adjusted trial estimate in the same sentence as if one disproves the other. State what population each result can and cannot represent.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- A statistic is presented without its population, duration, or outcome definition-
A trial’s absence of a signal is rewritten as proof that a symptom cannot occur
-
A self-selected survey is used to estimate population prevalence
-
Withdrawal and relapse are treated as mutually exclusive or diagnosable from timing alone
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- What is the current indication and treatment goal?
- Which alternative explanations for the symptoms need assessment?
- What is the exact medication, formulation, timing, and most recent change?
- Which outcome should be monitored before another change is considered?
- What are the urgent warning signs and the fastest route back to the clinical team?
Frequently asked questions
Is 15% the true withdrawal rate?
It is one placebo-adjusted average estimate from a 2024 meta-analysis, not a universal rate for every drug, duration, taper method, or population.
Does the 2025 meta-analysis prove withdrawal is mild?
It describes average outcomes in included trials. It does not settle severe long-term cases, persistent symptoms, or all real-world medication patterns.
Are patient surveys useless?
No. They identify experiences, language, severity, and research gaps. They generally cannot estimate population incidence without representative sampling and controls.
Can two contradictory-looking studies both be useful?
Yes, when they answer different questions. The task is to define the question and population rather than choose a preferred headline.
Regional and formulation note
Guidelines, labels, formulations, and care pathways vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
Henssler J, et al. Incidence of antidepressant discontinuation symptoms: a systematic review and meta-analysis. The Lancet Psychiatry. 2024. Evidence type: Systematic review and meta-analysis. Use in this article: Estimated incidence after accounting for nonspecific symptoms; important limits include treatment duration and study design.
-
Kalfas M, et al. Incidence and Nature of Antidepressant Discontinuation Symptoms: A Systematic Review and Meta-Analysis. JAMA Psychiatry. 2025. Evidence type: Systematic review and meta-analysis. Use in this article: Placebo-controlled symptom estimates, largely from relatively short trials; does not settle long-term or persistent-withdrawal questions.
-
Horowitz MA, et al. Antidepressant withdrawal and duration of use: observational evidence. 2025. Evidence type: Observational study. Use in this article: Patient-reported associations; useful for hypothesis generation but vulnerable to selection and recall bias.
-
Rennwald K, Hengartner MP. Persistent post-withdrawal symptoms after antidepressants: systematic review. 2025. Evidence type: Systematic review. Use in this article: Shows that the persistent-withdrawal evidence base remains sparse and methodologically limited.
-
Zaccoletti D, et al. Comparison of antidepressant deprescribing strategies: systematic review and network meta-analysis. The Lancet Psychiatry. 2026. Evidence type: Systematic review and network meta-analysis. Use in this article: Supports slow tapering combined with psychological support for relapse prevention, while certainty varies and withdrawal-specific outcomes remain incomplete.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.