 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
Direct Benzodiazepine Taper vs Diazepam Substitution: What the 2025 Guideline Says
Key answer
A comparison of direct benzodiazepine tapering and transition to diazepam or another longer-acting medication, including the limits of equivalence tables. The central safety principle is: Reduces the current benzodiazepine; avoids conversion uncertainty but may be limited by short half-life or available strengths. [1–3]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| Direct taper | Reduces the current benzodiazepine; avoids conversion uncertainty but may be limited by short half-life or available strengths. |
| Long-acting substitution | May smooth exposure and offer smaller dose options, but adds conversion uncertainty, accumulation, interaction, and organ-function concerns. |
| Guideline position | Consider individual factors; substitution is not required for every patient. |
| Equivalence | Approximate clinical range, not exact milligram identity. |
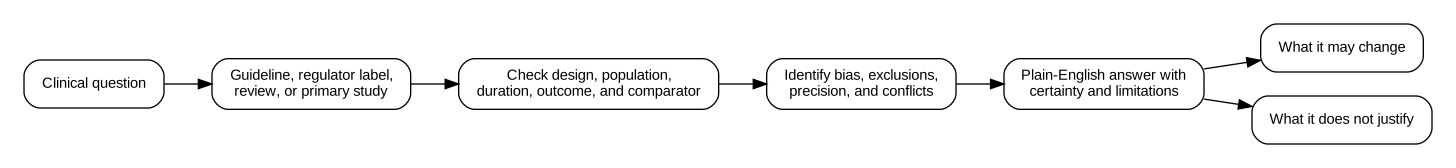
Evidence basis and uncertainty
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–3]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Multisociety clinical practice guideline | Recommends individualized, generally gradual reductions, monitoring, and avoidance of abrupt discontinuation in physically dependent patients. |
| 2 | Historical expert manual | Influential practical resource; not a current multisociety evidence-graded guideline and not mandatory for every patient. |
| 3 | Guideline | Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
What a direct taper means
A direct taper keeps the current benzodiazepine and reduces it in planned steps. Advantages include avoiding a new medication and preserving a known response. Challenges include short dosing intervals, interdose symptoms, small available strengths, and formulations that are difficult to measure accurately.
Why diazepam is considered
Diazepam has a long half-life and active metabolites, which can smooth concentration changes and provide small tablet or liquid options in some regions. It may be less suitable in significant liver impairment, frailty, older age, pregnancy contexts, or when accumulation and sedation are concerns.
Why conversion tables are estimates
Equivalence tables combine pharmacology, clinical experience, and population averages. Potency, receptor effects, active metabolites, dosing pattern, indication, and individual response differ. A calculated equivalent may over-sedate one person and under-cover another.
How the 2025 guideline changes the conversation
The multisociety guideline supports individualized planning, generally gradual initial reductions, monitoring at every step, and slowing or pausing when clinically indicated. It does not require diazepam substitution and does not turn a suggested starting range into a universal schedule.
What should drive the choice
Consider current benzodiazepine, duration, dose pattern, prior withdrawal, seizure history, alcohol and opioid use, liver and kidney function, age, pregnancy, formulation access, driving or occupational risk, and the person’s preference. The plan should include what happens if the transition itself causes instability.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- Seizure, delirium, hallucinations, or severe confusion-
Conversion causes profound sedation or uncontrolled withdrawal
-
Concurrent opioid, alcohol, or other sedative use with breathing impairment
-
Significant liver disease or frailty is ignored in a diazepam plan
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- What is the current indication and treatment goal?
- Which alternative explanations for the symptoms need assessment?
- What is the exact medication, formulation, timing, and most recent change?
- Which outcome should be monitored before another change is considered?
- What are the urgent warning signs and the fastest route back to the clinical team?
Frequently asked questions
Is diazepam always easier to taper?
No. Some people benefit from its long half-life; others experience accumulation, sedation, a poor conversion, or contraindications.
Can an online calculator convert my dose exactly?
No. Calculators use approximate equivalence tables and cannot account for individual response or clinical context.
Does the Ashton Manual conflict with ASAM?
They overlap on gradual patient-centered reduction, but the Ashton Manual is an older expert resource and emphasizes diazepam substitution more strongly than the 2025 guideline.
Can I cross over one dose at a time?
That is one clinical strategy, but the sequence and monitoring are individualized and should be supervised.
Regional and formulation note
Guidelines, labels, formulations, and care pathways vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
ASAM and partner societies. Joint Clinical Practice Guideline on Benzodiazepine Tapering. 2025. Evidence type: Multisociety clinical practice guideline. Use in this article: Recommends individualized, generally gradual reductions, monitoring, and avoidance of abrupt discontinuation in physically dependent patients.
-
Ashton H. Benzodiazepines: How They Work and How to Withdraw (The Ashton Manual). Evidence type: Historical expert manual. Use in this article: Influential practical resource; not a current multisociety evidence-graded guideline and not mandatory for every patient.
-
NICE. Medicines associated with dependence or withdrawal symptoms: safe prescribing and withdrawal management for adults (NG215). Evidence type: Guideline. Use in this article: Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.