 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
Benzodiazepine Dose Equivalence: Why Conversion Tables Are Only Estimates
Key answer
How benzodiazepine equivalence tables are constructed, why values differ, and why a calculated diazepam equivalent is not a personal conversion dose. The central safety principle is: An approximate clinical comparison, often expressed as a diazepam-equivalent range. [1–3]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| What equivalence means | An approximate clinical comparison, often expressed as a diazepam-equivalent range. |
| Why tables differ | Different endpoints, studies, populations, indications, metabolites, and expert judgments. |
| What a calculator misses | Tolerance, dosing interval, organ function, age, interactions, and individual response. |
| Safe use | A starting reference for clinician monitoring, not an exact self-conversion. |
Evidence basis and uncertainty
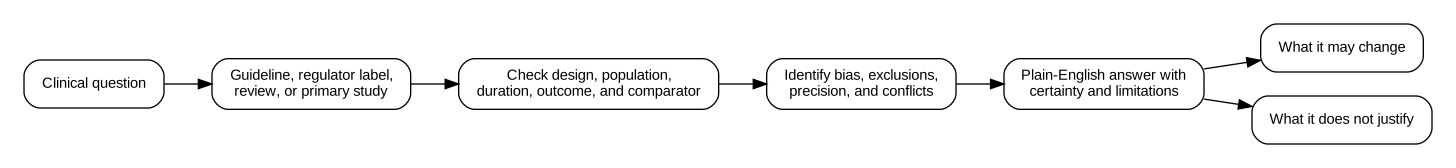
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–3]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Multisociety clinical practice guideline | Recommends individualized, generally gradual reductions, monitoring, and avoidance of abrupt discontinuation in physically dependent patients. |
| 2 | Historical expert manual | Influential practical resource; not a current multisociety evidence-graded guideline and not mandatory for every patient. |
| 3 | Guideline | Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
There is no single biologic exchange rate
Benzodiazepines differ in receptor affinity, speed of absorption, half-life, active metabolites, lipid solubility, dosing frequency, and clinical indication. An equivalent for anxiety may not feel equivalent for sedation, seizure control, muscle relaxation, or interdose symptoms.
How tables are built
Tables draw on pharmacology, clinical trials, withdrawal experience, therapeutic dose ranges, and expert consensus. Some provide one number; others provide a range. Precision to a decimal place can create false confidence when the underlying estimate is broad.
Why a calculated conversion can fail
A person may be over-sedated after a nominally equivalent long-acting dose or experience withdrawal because the conversion underestimates their response. Liver impairment, older age, smoking, enzyme inhibitors, opioids, and alcohol can change risk.
How clinicians reduce conversion risk
Clinicians may use staged substitution, monitor sedation and withdrawal, adjust for organ function, and preserve the option to pause. The transition itself is a medication change and should be separated from later taper reductions when feasible.
How to present equivalence on RxDown
Display ranges, source, version, and a prominent “not an exact conversion” warning. Do not let the app automatically prescribe a target dose. Any calculator should support clinician discussion and record uncertainty.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- A calculated conversion produces profound sedation or uncontrolled withdrawal-
The person has significant liver disease, frailty, or respiratory-depressant co-use
-
The table source and version are unknown
-
A calculator output is treated as a prescription
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- What is the current indication and treatment goal?
- Which alternative explanations for the symptoms need assessment?
- What is the exact medication, formulation, timing, and most recent change?
- Which outcome should be monitored before another change is considered?
- What are the urgent warning signs and the fastest route back to the clinical team?
Frequently asked questions
Why do two reputable tables disagree?
They may use different evidence and endpoints. The disagreement reflects uncertainty rather than one table necessarily being fraudulent.
Is a diazepam-equivalent dose equally sedating?
Not necessarily. Sedation, anxiety control, and withdrawal coverage are not identical endpoints.
Can I convert all at once?
That may be unsafe for some people. The strategy and monitoring should be individualized.
Should RxDown show a calculator?
Only with ranges, assumptions, source dates, and a clinician-review workflow—not as an instruction engine.
Regional and formulation note
Guidelines, labels, formulations, and care pathways vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
ASAM and partner societies. Joint Clinical Practice Guideline on Benzodiazepine Tapering. 2025. Evidence type: Multisociety clinical practice guideline. Use in this article: Recommends individualized, generally gradual reductions, monitoring, and avoidance of abrupt discontinuation in physically dependent patients.
-
Ashton H. Benzodiazepines: How They Work and How to Withdraw (The Ashton Manual). Evidence type: Historical expert manual. Use in this article: Influential practical resource; not a current multisociety evidence-graded guideline and not mandatory for every patient.
-
NICE. Medicines associated with dependence or withdrawal symptoms: safe prescribing and withdrawal management for adults (NG215). Evidence type: Guideline. Use in this article: Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.