 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
ASAM 2025 vs the Ashton Manual: What Changed, What Stayed, and Where Evidence Is Limited
Key answer
The 2025 ASAM-led guideline and the Ashton Manual share a patient-centered gradual approach, but the newer guideline uses formal consensus and evidence grading, covers broader populations and settings, and treats long-acting substitution as optional rather than universal. The practical interpretation must remain within the population, duration, formulation, and outcomes that were actually studied. [1–2]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| One-sentence finding | The 2025 ASAM-led guideline and the Ashton Manual share a patient-centered gradual approach, but the newer guideline uses formal consensus and evidence grading, covers broader populations and settings, and treats long-acting substitution as optional rather than universal. [1–2] |
| Evidence base | The Ashton Manual is an expert clinical resource derived from a withdrawal clinic and published protocols. The 2025 guideline was developed by multiple professional societies using systematic evidence review, consensus methods, and recommendations spanning outpatient, inpatient, pregnancy, older adults, substance use, and co-prescribing. [1–2] |
| Main uncertainty | High-quality comparative taper trials remain limited, so many recommendations rely on lower-certainty evidence and clinical consensus. The Ashton schedules are examples, not validated universal protocols. The newer guideline does not answer every formulation or persistent-symptom question. [1–2] |
| Practice implication | Use the 2025 guideline as the current clinical anchor and the Ashton Manual as historical and practical context. Explain differences in evidence status. Never reproduce a sample schedule as a personal prescription. [1–2] |
| Not justified | The comparison does not justify dismissing patient experience, requiring diazepam conversion, applying a 5–10% range rigidly, or assuming that a guideline guarantees a symptom-free taper. [1–2] |
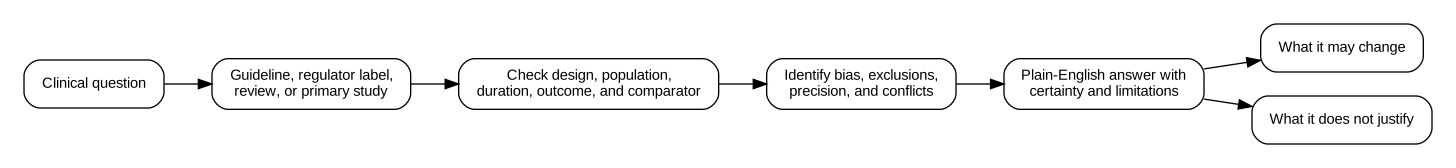
Evidence basis and uncertainty
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–2]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Multisociety clinical practice guideline | Recommends individualized, generally gradual reductions, monitoring, and avoidance of abrupt discontinuation in physically dependent patients. |
| 2 | Historical expert manual | Influential practical resource; not a current multisociety evidence-graded guideline and not mandatory for every patient. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
The finding in one sentence
The 2025 ASAM-led guideline and the Ashton Manual share a patient-centered gradual approach, but the newer guideline uses formal consensus and evidence grading, covers broader populations and settings, and treats long-acting substitution as optional rather than universal.
Why this question matters
The Ashton Manual remains highly influential among patients and clinicians, while the 2025 guideline is now the principal current US multisociety reference. Presenting one as entirely right and the other obsolete would lose useful context.
What evidence was reviewed
The Ashton Manual is an expert clinical resource derived from a withdrawal clinic and published protocols. The 2025 guideline was developed by multiple professional societies using systematic evidence review, consensus methods, and recommendations spanning outpatient, inpatient, pregnancy, older adults, substance use, and co-prescribing.
What the studies found
Both emphasize avoiding abrupt discontinuation, respecting individual variation, and slowing when symptoms are significant. The 2025 guideline proposes cautious starting ranges rather than fixed schedules and highlights shared decision-making, level-of-care assessment, overdose risk, and optional transition to a longer-acting benzodiazepine.
Key limitations and sources of uncertainty
High-quality comparative taper trials remain limited, so many recommendations rely on lower-certainty evidence and clinical consensus. The Ashton schedules are examples, not validated universal protocols. The newer guideline does not answer every formulation or persistent-symptom question.
What this may change in practice
Use the 2025 guideline as the current clinical anchor and the Ashton Manual as historical and practical context. Explain differences in evidence status. Never reproduce a sample schedule as a personal prescription.
What the evidence does not justify
The comparison does not justify dismissing patient experience, requiring diazepam conversion, applying a 5–10% range rigidly, or assuming that a guideline guarantees a symptom-free taper.
What research should do next
Comparative pragmatic trials should evaluate direct versus substitution strategies, taper pace, formulations, behavioral support, severe withdrawal, patient-reported function, and long-term outcomes.
Funding and conflict-of-interest note
Drug-development studies are often sponsored by manufacturers, while guideline panels and independent reviews can also include authors with industry relationships. Publication should list the funding source and declared conflicts for every pivotal study. A declared conflict does not invalidate a result, but it raises the importance of protocol registration, complete outcome reporting, independent replication, and separation of evidence from promotional language.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- A trial result is described as proof for populations, durations, doses, or combinations that were not studied-
Absence of a detected signal is rewritten as a categorical absence-of-risk claim
-
A network meta-analysis is presented as a head-to-head randomized comparison
-
Regulatory approval in one country is described as global approval
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- Does this evidence apply to my diagnosis, age, treatment duration, formulation, and other medications?
- Was the finding based on a randomized comparison, an indirect comparison, an observational study, or mechanistic modeling?
- Were withdrawal, relapse, function, serious adverse events, and long-term outcomes measured directly?
- What was not studied, and what uncertainty remains for my situation?
- Would this finding actually change a clinical decision, or only support further research?
Frequently asked questions
Is the Ashton Manual obsolete?
No. It remains influential, but it is not a current evidence-graded multisociety guideline.
Does ASAM reject diazepam substitution?
No. It treats transition to a longer-acting benzodiazepine as an option based on individual factors.
Which schedule should a website publish?
No individualized schedule. Publish principles, evidence status, and clinician discussion points.
Why are recommendations not more precise?
Comparative evidence is limited and patient variability is high.
Regional and formulation note
Approval status, labels, and clinical practice vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
ASAM and partner societies. Joint Clinical Practice Guideline on Benzodiazepine Tapering. 2025. Evidence type: Multisociety clinical practice guideline. Use in this article: Recommends individualized, generally gradual reductions, monitoring, and avoidance of abrupt discontinuation in physically dependent patients.
-
Ashton H. Benzodiazepines: How They Work and How to Withdraw (The Ashton Manual). Evidence type: Historical expert manual. Use in this article: Influential practical resource; not a current multisociety evidence-graded guideline and not mandatory for every patient.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.