 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
Corticosteroid Tapering: Adrenal Suppression, Disease Flare, and Emergency Symptoms
Key answer
A high-risk specialist guide to systemic corticosteroid tapering, distinguishing adrenal insufficiency, glucocorticoid withdrawal syndrome, and recurrence of the treated inflammatory disease. The central safety principle is: Adrenal insufficiency, glucocorticoid withdrawal syndrome, and flare of the treated disease can produce similar symptoms. [1]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| Three overlapping problems | Adrenal insufficiency, glucocorticoid withdrawal syndrome, and flare of the treated disease can produce similar symptoms. |
| Risk depends on | Systemic exposure, dose, duration, potency, timing, repeated courses, route, interacting medicines, and individual susceptibility. |
| Emergency concern | Adrenal crisis can involve severe weakness, vomiting, abdominal pain, low blood pressure, confusion, or collapse. |
| What a website must not do | Generate a prednisone schedule without the indication, current disease control, total exposure, and adrenal-risk assessment. |
Evidence basis and uncertainty
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Clinical practice guideline | Tapering depends on disease control, dose, duration, adrenal suppression, and symptoms; abrupt stopping can be dangerous. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
Why “steroid taper” is not one calculation
Prednisone, prednisolone, dexamethasone, methylprednisolone, hydrocortisone, and other corticosteroids differ in potency and duration. Systemic exposure can also come from injections, inhaled, topical, ocular, or nasal products, especially at high doses or with interacting medicines. The inflammatory disease may require one pace while recovery of the hypothalamic–pituitary–adrenal axis requires another.
Adrenal insufficiency, withdrawal syndrome, or disease flare?
Fatigue, weakness, muscle or joint pain, nausea, appetite change, low mood, and sleep disturbance can overlap. Disease-specific signs may support a flare, while low blood pressure, vomiting, low sodium, low glucose, or collapse raise concern for adrenal insufficiency. Symptoms alone may not separate them, and testing must be interpreted in clinical context.
What specialist planning includes
Review the original disease, current control, cumulative and recent exposure, time of dosing, other steroid routes, CYP3A interactions, previous adrenal testing, and upcoming surgery or illness. The plan may include stress-dose education, a steroid emergency card or medical alert, and instructions for vomiting or acute illness. Exact recommendations vary by country and patient.
Why abrupt stopping can be dangerous
After sufficient exposure, endogenous cortisol production may be suppressed. Abrupt removal can leave the body unable to meet baseline or stress needs. The absence of obvious Cushingoid features does not exclude suppression. Conversely, unnecessary prolonged corticosteroid exposure has important harms, so the answer is individualized reduction and monitoring rather than indefinite continuation.
Evidence limits
Guideline thresholds describe risk categories, not a perfect prediction for every person. Recovery time varies substantially. A public article should explain principles and emergency signs but must not substitute for the treating specialist or endocrinology assessment.
When urgent medical assessment may be needed
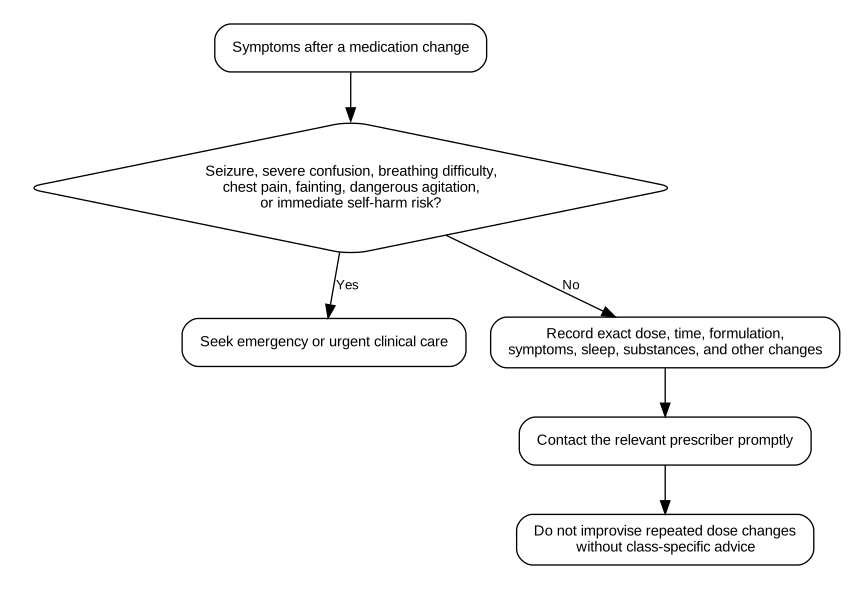
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- Severe weakness with vomiting, abdominal pain, low blood pressure, confusion, or collapse-
Inability to keep corticosteroid medication down during acute illness
-
Rapid worsening of the treated inflammatory disease with breathing, neurologic, or organ-threatening symptoms
-
Upcoming surgery or severe infection without a documented steroid stress plan
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- What is the current indication and treatment goal?
- Which alternative explanations for the symptoms need assessment?
- What is the exact medication, formulation, timing, and most recent change?
- Which outcome should be monitored before another change is considered?
- What are the urgent warning signs and the fastest route back to the clinical team?
Frequently asked questions
Is a short steroid course always safe to stop?
Many short courses can be stopped as prescribed, but repeated courses, high exposure, recent long-term treatment, interactions, and individual factors can change risk.
Are inhaled or topical steroids irrelevant?
No. They usually create less systemic exposure, but high doses, large areas, prolonged use, and interactions can matter.
What is stress dosing?
Temporary additional glucocorticoid during illness, surgery, or physiologic stress for people at risk; instructions must come from the clinical team.
Can fatigue alone diagnose adrenal insufficiency?
No. It is nonspecific and requires clinical assessment, sometimes including laboratory testing.
Regional and formulation note
Guidelines, labels, formulations, and care pathways vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
- European Society of Endocrinology and Endocrine Society Joint Guideline: Glucocorticoid-induced adrenal insufficiency. 2024. Evidence type: Clinical practice guideline. Use in this article: Tapering depends on disease control, dose, duration, adrenal suppression, and symptoms; abrupt stopping can be dangerous.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.