 RxDown
Evidence reviewed through:
⚕️ This article is education, not medical advice. Every claim is sourced below. Never stop or change medication without your prescriber — some medications are dangerous to stop abruptly.
Bupropion (Wellbutrin) Withdrawal: How Its Discontinuation Profile Differs
This article uses the generic name bupropion as the canonical medication entity. Wellbutrin appears only as a United States brand-name search synonym; the body does not alternate between the two names.
Key answer
Bupropion dose changes should be individualized around the indication, exact formulation, exposure history, co-medications, and the risks of both continuing and changing treatment. Symptoms after a missed dose, dose reduction, formulation switch, or stop can reflect withdrawal, rebound, relapse, an adverse effect, or an unrelated medical problem; a prescriber should interpret the timeline rather than relying on a universal internet schedule. [1–4]
A safe interpretation starts with the exact medication or intervention, the reason it is being used, the formulation, treatment duration, other medicines, current symptoms, and the risks of both continuing and changing treatment. The article therefore explains decision factors and safety boundaries rather than prescribing a fixed schedule.
At a glance
| Question or decision | Evidence-based answer |
|---|---|
| Canonical name used in this article | bupropion |
| Medication class | norepinephrine–dopamine reuptake inhibitor antidepressant [1] |
| Pharmacokinetic context | Bupropion has an average half-life around 21 hours, while active metabolites may persist longer. [1] |
| Formulation issue | Immediate-release, sustained-release, and extended-release products have different dosing properties. Sustained- and extended-release tablets should generally be swallowed whole because crushing or splitting can alter release and raise peak exposure and seizure risk. [1] |
| Commonly reported symptom domains | Irritability, anxiety, sleep change, headache, fatigue, mood change, and difficulty concentrating [1] |
| Main safety issue | Seizure, severe agitation, mania, suicidality, or an unsafe change in alcohol or sedative use needs urgent review. [1] |
| Personalized schedule provided? | No. The article explains decision factors and safety boundaries, not an individualized dose plan. |
Evidence basis and uncertainty
This article prioritizes regulator-hosted product information, current clinical guidance, systematic reviews, randomized trials, and carefully labeled observational or mechanistic evidence. The references below are used according to their design and limitations [1–4]. Absence of a detected signal is not rewritten as absence of risk, and a population average is not presented as an individual prediction.
| Reference | Evidence type | How it is used in this article |
|---|---|---|
| 1 | Regulator-hosted product labeling | Verify the exact manufacturer, formulation, strength, and country before any formulation advice. |
| 2 | Professional guidance | Patient-facing guidance on withdrawal, proportional reductions, and formulation considerations. |
| 3 | Guideline | Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse. |
| 4 | Systematic review | Found limited evidence on the accuracy and safety of dose-form manipulation; product-specific verification remains essential. |
Working definitions
| Term | Meaning in this article |
|---|---|
| Withdrawal symptoms | New or intensified symptoms after a dose reduction, missed dose, formulation change, or stop when physiologic adaptation is a plausible contributor. |
| Rebound | Temporary return of a treated symptom above its pretreatment baseline. |
| Relapse or recurrence | Return of the underlying treated condition. |
| Physical dependence | Physiologic adaptation; it is not the same as addiction or a substance use disorder. |
What is distinctive about this medication?
Bupropion does not primarily act through serotonin reuptake, so its reported discontinuation pattern may differ from SSRIs and SNRIs. Evidence is less extensive, which is not the same as proving that withdrawal cannot occur.
Pharmacokinetic context: Bupropion has an average half-life around 21 hours, while active metabolites may persist longer. Pharmacokinetic averages describe groups, not a personal countdown. Age, liver or kidney function, genetic metabolism, interacting medicines, adherence, and formulation can change exposure.
Possible symptoms after a reduction or stop
Reports and product information may include irritability, anxiety, sleep change, headache, fatigue, mood change, and difficulty concentrating. These symptoms are not specific enough to diagnose withdrawal by themselves. The strongest clues are a plausible medication change, a compatible time relationship, a symptom pattern that differs from the original condition, and what happens over time.
Physical dependence means the body has adapted to repeated exposure. It is not the same as addiction or a substance use disorder. A person may have physical dependence without craving, loss of control, compulsive use, or continued use despite harm.
Why there is no universal timeline
A fixed “day 1 to day 14” timeline can mislead. Changes may emerge over days as bupropion and active metabolites decline. The extended-release formulation does not make tablet manipulation safe.
Earlier symptoms may be more likely after a missed dose or faster fall in exposure. Delayed symptoms can occur when the medication or active metabolites persist. Symptoms may also fluctuate, and the treated condition can recur during the same period. Timing is useful evidence, but it is not a stand-alone diagnosis.
Formulation and small-dose questions
Immediate-release, sustained-release, and extended-release products have different dosing properties. Sustained- and extended-release tablets should generally be swallowed whole because crushing or splitting can alter release and raise peak exposure and seizure risk.
The exact product matters. Modified-release, delayed-release, enteric-coated, orally disintegrating, liquid, capsule, and long-acting products cannot be treated as interchangeable. Do not split, crush, open, dissolve, or count capsule contents unless the product label and a pharmacist confirm that the method is appropriate and sufficiently accurate. Published evidence on tiny-dose manipulation remains limited, so consistency and verification matter.
Withdrawal, rebound, relapse, or something else?
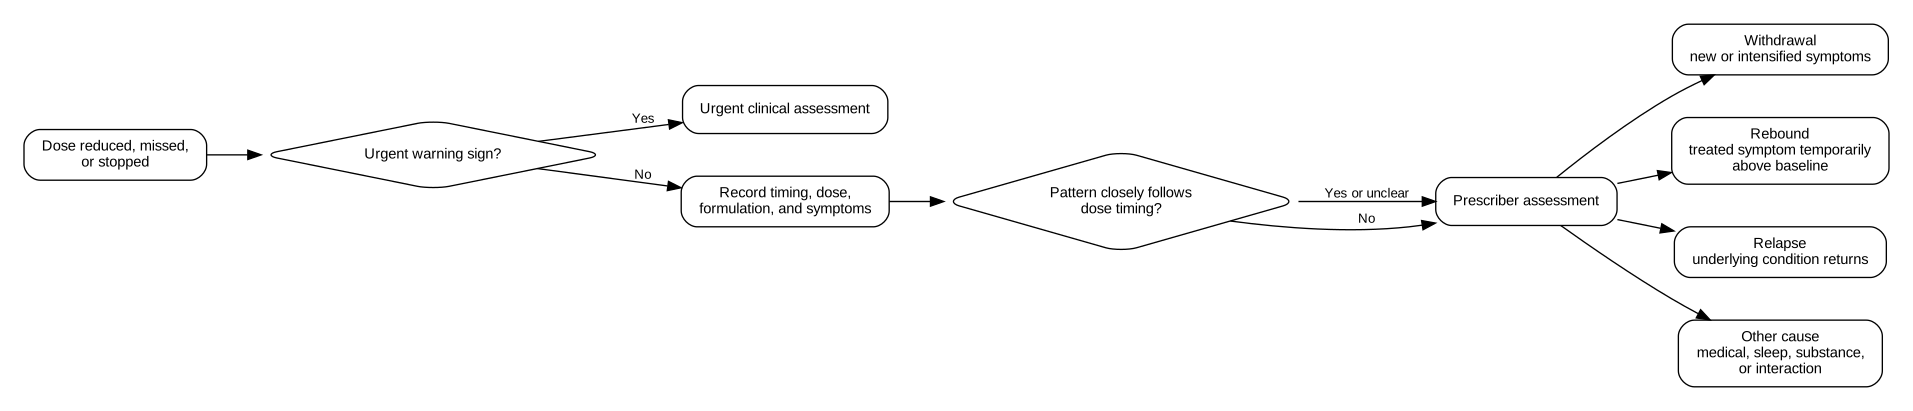
Withdrawal means new or intensified symptoms after reducing or stopping a medication to which the body has adapted. Rebound means a treated symptom temporarily returns above its pre-treatment baseline. Relapse means the underlying condition is recurring. More than one can occur together.
Fatigue, concentration problems, low motivation, and mood change may resemble the original depression or nicotine-withdrawal symptoms if bupropion was used for smoking cessation.
Other possibilities include infection, dehydration, endocrine or neurologic illness, sleep deprivation, alcohol or other substance effects, a new medication, an interaction, or inconsistent dosing. This is why symptom tracking should support clinical assessment rather than replace it.
What a prescriber-led plan should consider
A clinically sound plan usually starts with the current indication, benefit, duration of use, previous missed-dose or reduction reactions, exact formulation, other medications, pregnancy status, organ function where relevant, and the risks of both continuing and changing treatment.
The indication and formulation are essential. The prescriber should assess seizure risk factors, alcohol use, eating disorders, interacting medicines, and whether the medication was used for depression, seasonal affective disorder, or smoking cessation.
The goal is not to force a predetermined speed. The plan should define what will be monitored, how the person can contact the prescriber, what would justify pausing or reassessment, and which symptoms need urgent evaluation. Repeated unsupervised dose changes can make timing harder to interpret.
What to record before contacting the prescriber
Record the exact generic name, manufacturer if known, formulation, strength, total daily dose, dose times, date and size of the last change, missed doses, new medicines or supplements, alcohol or other sedatives, sleep timing, and the onset and functional impact of each symptom. Also record what the original condition looked like before treatment. A concise timeline is more useful than a single symptom score.
What the evidence supports—and what it does not prove
The product label and class-specific guidance support recognizing possible symptoms after reduction and avoiding abrupt changes when clinically important physical dependence or relapse risk is present. Bupropion-specific discontinuation evidence is limited, and absence of a large trial signal does not establish zero individual risk.
Evidence from clinical trials often reflects selected participants, limited treatment durations, protocol-defined reductions, and short follow-up. Post-marketing reports can detect rare or delayed problems but cannot establish incidence by themselves. Neither source can predict one person’s course with certainty.
When urgent medical assessment may be needed
    Seek urgent local medical assessment when any of the following applies. This list is intentionally conservative and is not a diagnostic checklist:

- Seizure or loss of consciousness-
Immediate self-harm risk
-
Mania, psychosis, or severe agitation
-
Abrupt alcohol or sedative withdrawal occurring at the same time
Emergency pathways and telephone numbers vary by country. A tracking application or educational article cannot rule out an emergency.
Questions to take to the prescriber
- What indication is bupropion treating now, and what are the risks of continuing versus changing it?
- Which exact manufacturer, formulation, and strength am I taking, and what smaller-dose options are product-appropriate?
- Which symptoms and functional outcomes should we monitor, and how can I contact the prescriber between visits?
- What findings would justify pausing, changing the plan, or urgent assessment?
- How will we distinguish withdrawal, rebound, relapse, an adverse effect, and an unrelated medical problem?
Frequently asked questions
Can bupropion withdrawal be diagnosed from symptoms alone?
No. Symptoms overlap with rebound, relapse, adverse effects, sleep loss, substance effects, and medical illness. Timing and clinical context are required.
Does the average half-life tell me exactly when symptoms will start?
No. It is a population average and does not account for active metabolites, formulation, dose pattern, organ function, interactions, or individual variability.
Should I skip days to make the dose smaller?
Usually this should not be improvised. Skipping days can create larger exposure swings, especially for shorter-acting medicines. A pharmacist and prescriber should identify product-appropriate ways to make smaller, consistent doses.
Can I crush, split, open, or dissolve bupropion?
Only when the exact product labeling and a pharmacist confirm that the method is suitable. The answer can differ between manufacturers, strengths, and immediate- versus modified-release products.
Does having withdrawal symptoms mean addiction?
No. Physical dependence and withdrawal can occur without the behavioral features of addiction or a substance use disorder.
Regional and formulation note
Brand names, formulations, strengths, and labeling vary by country. Verify the exact product label, manufacturer, strength, release system, and local clinical pathway before use. A tablet or capsule instruction that is correct for one product may be wrong for another.
References
-
US prescribing information and DailyMed product records for bupropion. Evidence type: Regulator-hosted product labeling. Use in this article: Verify the exact manufacturer, formulation, strength, and country before any formulation advice.
-
Royal College of Psychiatrists. Stopping antidepressants. Evidence type: Professional guidance. Use in this article: Patient-facing guidance on withdrawal, proportional reductions, and formulation considerations.
-
NICE. Medicines associated with dependence or withdrawal symptoms: safe prescribing and withdrawal management for adults (NG215). Evidence type: Guideline. Use in this article: Individualized planning, slow stepwise reduction, monitoring, and differentiation of withdrawal from relapse.
-
O’Brien D, et al. A systematic review of manipulations to pharmaceutical dosage forms used in psychotropic tapering plans. 2025. Evidence type: Systematic review. Use in this article: Found limited evidence on the accuracy and safety of dose-form manipulation; product-specific verification remains essential.

Bring real data to your doctor
Generate a clinician-ready Doctor Report in SBAR format with trend charts, plus clean CSV and PDF exports. Walk into your next appointment with evidence, not guesswork.
RxDown is a data tracking and journaling tool for adults (18+). It does not provide medical advice, diagnosis, or treatment. Never stop taking medication or change your dose based solely on information from this app or website — medication reduction should always be supervised by a qualified healthcare professional.